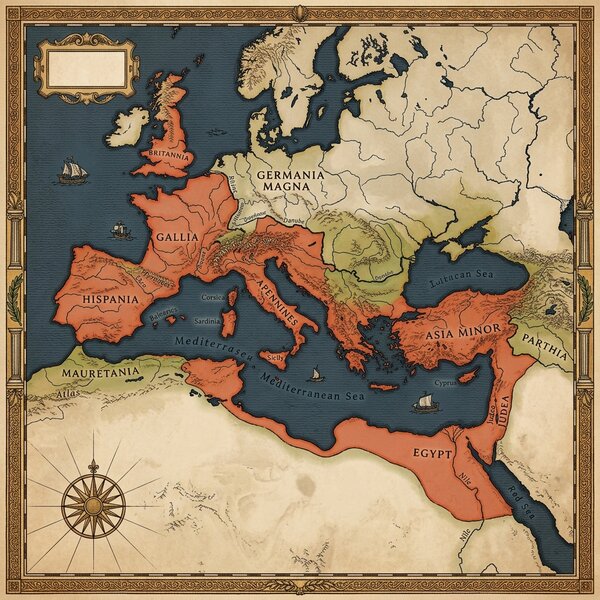
The plague is one of the most devastating infectious diseases in human history. Caused by the bacterium Yersinia pestis, it became known in the Middle Ages as the ‘Black Death’ – a name which, in English, became synonymous with the catastrophe of the 14th century. The Black Death reached Europe in 1347 and raged until 1353. During those few years, depending on the region, around one-third to one-half of the population died.

What you can expect in this article
- Key findings at a glance
- Introduction: What is the plague and why did it spread so rapidly?
- The pathogen: Yersinia pestis and its clinical presentation
- Early waves of the plague: The Justinian Plague as a precursor
- The origins of the Black Death: Central Asia, the Tian Shan and Lake Issyk-Kul
- The route to Europe: trade routes, the Black Sea and the siege of Caffa
- Spread across Europe 1347–1353: Chronology of the Black Death
- Routes of transmission and environmental factors: Why the plague spread so effectively
- Social reactions and misinterpretations: faith, panic and scapegoats
- Medical knowledge, measures and quarantine in the Middle Ages
- Demographic, economic and political consequences of the spread of the plague
- Recurring waves of the plague and the end of the great epidemics in Europe
- The Plague today: spread, modern medicine and the significance of history
- Conclusion: What the history of the spread of the plague teaches us
- Frequently asked questions about the spread of the plague (FAQ)
 Reading time approx. 17 mins.
Key findings at a glance
- The Black Death (1347–1353) fundamentally transformed Europe: according to estimates, between 25 and 50 million people died; the figure most commonly cited is between one-third and one-half of the European population, rising to as much as 60 per cent in particularly hard-hit areas.
- The pathogen, Yersinia pestis, originated in the Tian Shan mountains in Central Asia and spread via the trade routes of the Pax Mongolica to the Black Sea and from there to Europe.
- The clinical presentation of the plague comprises three main forms: bubonic plague, pneumonic plague and septicemic plague. In the Middle Ages, there was no knowledge whatsoever of bacteria, fleas as vectors, or effective countermeasures.
- Waves of the plague ravaged Europe right up until the 18th century, before improved hygiene, quarantine systems and, later, antibiotics largely brought the disease under control.
- Even today, cases of the plague still occur in some regions of the world, but with early diagnosis they can be effectively treated with antibiotics.
Introduction: What is the plague and why did it spread so rapidly?
This spread was no coincidence, but the result of a combination of several factors: the pathogen itself, its vectors such as rat fleas, social conditions such as overpopulation and poverty, and the extensive trade networks that had linked Asia, Europe and North Africa since the High Middle Ages. Port cities, marketplaces and pilgrimage routes provided ideal transport routes for the pathogen.
This article examines the history of the plague’s spread across Eurasia and North Africa: from its origins in the Central Asian steppes, through its devastating course in Europe, to modern insights. The focus is on the spread itself, its causes and consequences – not on a comprehensive history of medicine.
The pathogen: Yersinia pestis and its clinical presentation
Yersinia pestis is a Gram-negative bacterium belonging to the family Enterobacteriaceae. It was discovered in 1894 in Hong Kong by the Swiss physician and student of Pasteur, Alexandre Yersin, who isolated the pathogen within a few weeks during an outbreak of the third plague pandemic. Almost at the same time, the Japanese bacteriologist Kitasato Shibasaburō also described the pathogen, but his early reports remained contradictory, with the result that the scientific community generally attributes priority to Yersin – the bacterium was later named after him.
The natural reservoirs of the plague pathogen are primarily wild rodents. In Central Asia and Mongolia, Yersinia pestis continues to circulate in marmot populations to this day; in medieval Europe, the brown rat (Rattus rattus) played the central role. Fleas – in particular the rat flea Xenopsylla cheopis – transmitted the bacterium to humans whilst feeding on their blood.
The clinical presentation of the plague comprises three main forms:
- Bubonic plague: Painful swelling of the lymph nodes (buboes), high fever, chills. Swollen inguinal lymph nodes are typical, as are occasional dark patches of skin.
- Pneumonic plague: Caused by droplet transmission or, secondarily, via the bloodstream; it can spread directly from person to person – if left untreated, it is almost always fatal.
- Pestisepsis: Blood poisoning caused by Yersinia pestis, often without the classic buboes, with a rapid progression.
Historical accounts, such as those by Giovanni Boccaccio of Florence in 1348, describe fever, abscesses and shortness of breath – in retrospect, a clear clinical picture that can now be unambiguously identified. In the Middle Ages, however, there was no knowledge whatsoever of bacteria or vectors, which is why the actual routes of transmission remained a mystery.
Early waves of the plague: the Justinian Plague as a precursor

The history of the plague’s spread dates back well before the Black Death. As early as the 6th century, the plague struck the Byzantine Empire with full force: the Justinian Plague began around 541 AD and is regarded as the first comprehensively documented plague pandemic.
The Byzantine historian Procopius of Caesarea describes its point of origin as the port city of Pelusium in Egypt. From there, the pathogen spread via Alexandria and the Levant as far as Constantinople, the capital of the Eastern Roman Empire. According to Procopius, around one-fifth of the city’s population died there; on some days, several thousand people are said to have died – although modern historians consider the reported daily figures to be significantly exaggerated. The disease continued to spread along the Mediterranean coast to Italy, Gaul and Germania.
Recurring waves at intervals of around ten to fifteen years plagued the population until around 750 AD. The consequences were severe: a labour shortage in agriculture, the weakening of state structures and a noticeable decline in long-distance trade. Emperor Justinian was forced to witness how his plans for expansion were considerably hampered by the plague.
Why did the plague then disappear from Europe for centuries? Possible explanations range from changes in trade routes and climatic fluctuations to gaps in the written sources. This missing interim period explains, at least in part, why people in the 14th century were virtually defenceless against the new wave – there was no collective medical knowledge and no institutionalised epidemic control.
Origin of the Black Death: Central Asia, the Tian Shan and Lake Issyk-Kul
The origin of the Black Death has long been the subject of controversy. Hypotheses ranged from China, via the Qinghai-Tibetan Plateau, to the Black Sea. A genetic study published in 2022 in the journal *Nature* has significantly clarified the picture: the plague originated in the Tian Shan mountains in what is now Kyrgyzstan.
Teeth from seven deceased individuals from two burial grounds, Kara-Djigach and Burana, in the region around Lake Yssykköl were examined. Inscriptions on the gravestones date the deaths of these people to the years 1338 and 1339 and explicitly cite a plague as the cause. DNA analysis detected traces of Yersinia pestis in the teeth of three women from a Nestorian Christian community. The international research team classified the strain found as lying immediately before the evolutionary branching point that experts refer to as the ‘Great Polytomy’ – the node from which, shortly afterwards, both the Black Death strain and most of the plague strains existing today emerged.
In this region, Yersinia pestis is thought to have circulated within a local rodent reservoir. Climatic and environmental conditions influenced rodent populations: periods of drought and wetness created population pressure that could lead to so-called spillover events – during which the bacterium jumped to humans.
The Pax Mongolica – the relative political stability of the Mongol Empire in the 13th and early 14th centuries – created secure caravan routes from East Asia through Central Asia and far to the west. This flourishing long-distance trade enabled the pathogen to spread over a wide area. From the Tian Shan, the pathogen began to spread westwards – initially slowly, but then accelerating rapidly from around 1345 onwards.

The route to Europe: trade routes, the Black Sea and the siege of Kaffa
Around 1345, cases of the plague began to appear in the trading centres of the Golden Horde – along the Volga, in the Crimea, and in cities such as Sarai and Astrakhan. In 1346, the plague reached the borders of Europe. Wars and trading expeditions played a major role in its further spread, and the territory of the Golden Horde became a hub for the plague.
One frequently cited event is the siege of the Genoese trading post of Kaffa (now Feodosia) in the Crimea in 1346. The chronicler Gabriele de’ Mussi reported that soldiers of the Golden Horde under Khan Dschanibeg, who were suffering from the plague, had hurled corpses over the city walls using catapults in order to infect those under siege – a frequently cited early example of biological warfare. Historical research now views this account with great scepticism: de’ Mussi himself was not present in Kaffa during the siege, and several recent studies cast doubt on whether catapulting corpses was even feasible given the geography of Kaffa and the military technology available at the time. It is more likely that the plague reached Europe independently of this, via the already brisk trade and migration flows from the Crimea.
The actual catastrophe unfolded on ships. Genoese and Venetian merchant ships from Kaffa and other Black Sea ports called at Constantinople, Messina, Genoa and Marseille, amongst other places, in the autumn of 1347. Port cities thus became the starting points for new outbreaks, from where the disease spread inland via sea and land routes – for example, to the Rhône Valley, the Po Valley and the Danube region.
Initial attempts at quarantine in individual port cities did provide some containment. However, this did little to stop the rats and fleas on board the ships: the plague travelled unseen in cargo holds and sacks of grain.
Spread across Europe 1347–1353: Chronology of the Black Death
The actual plague pandemic in Europe began in 1347 and ended in 1353. During these years, the first major wave of the Black Death swept across almost the entire continent. The trade routes linking Europe, Asia and North Africa in the Middle Ages became veritable highways for the plague.
1347: In October, the plague reached Messina in Sicily via Genoese ships. Within a few weeks, it had spread to Genoa and Marseille. Via Barcelona and Valencia, it swept across the Iberian Peninsula; via Constantinople, it reached the eastern Mediterranean.
1348: In this year, the epidemic reached northern Italy. In Florence, many people shunned even close relatives – Boccaccio recorded such scenes in his ‘Decameron’. Southern France, Provence and the Rhône Valley were severely affected. At the same time, the plague reached England: first Melcombe Regis in Dorset and the region around Bristol, and shortly afterwards London. Parts of the Holy Roman Empire had also already been affected.
1349–1350: The plague spread deep into Central Europe. Cities such as Cologne, Strasbourg, Nuremberg and Hamburg suffered massive losses. Switzerland, the Netherlands and Flanders were also affected. In Scandinavia – Norway and Sweden – the plague also claimed countless victims, and the rest of England was not spared either.
1351–1353: The plague reached Eastern Europe – Poland, Hungary and Russia. In some regions, such as parts of Bohemia, the spread was less severe – possibly due to lower population density or more effective containment measures.
Overall, estimates put the death toll in Europe at between 25 and 50 million; it is generally thought that between a third and a half of the population died, rising to as much as 60 per cent in particularly hard-hit regions and cities. Cities such as Munich, Frankfurt and Leipzig also suffered drastic population losses.
Routes of transmission and environmental factors: why the plague spread so effectively

The classic routes of transmission of the plague are now well understood. The rat flea Xenopsylla cheopis transmitted Yersinia pestis to humans whilst feeding on their blood. Once the lungs were infected, the disease was also transmitted via droplet infection directly from person to person.
Poor hygiene created favourable conditions for the proliferation of rats and fleas. Medieval towns offered virtually ideal conditions for the spread of the disease: densely packed buildings, open rubbish heaps, granaries and muddy streets. Rats found plenty of food, and their fleas easily jumped onto people, who often lived in close proximity.
High population density further facilitated the spread. In densely populated neighbourhoods of cities such as London, Florence or Hamburg, the pathogen had an easy time of it. Recent research suggests that, in addition to rat fleas, human ectoparasites – body lice and human fleas – may also have acted as co-vectors, particularly within households and during close contact between people.
Climatic and ecological factors also likely played a role. Researchers suspect that cycles of drought and wetness in Central Asia in the years around 1340 to 1345 put rodent populations under stress. Mass mortality among rodents drove their fleas to seek new hosts – including humans.
In the Middle Ages itself, however, the so-called miasma theory prevailed: it was believed that ‘bad air’ from the East was the cause of the plague. This misconception prevented effective countermeasures and facilitated the further spread of the disease.
Social reactions and misinterpretations: faith, panic and scapegoats
With no knowledge whatsoever of the pathogen, people sought explanations. For many, the answer was obvious: they interpreted the plague as God’s punishment. This belief had far-reaching consequences.
Prayer services and processions increased, as did the veneration of plague saints such as Rochus, Sebastian and Mary. The Church’s trade in indulgences also experienced a boom during the plague – the hope for divine grace became a business. Flagellants marched through the towns in organised processions and publicly flogged themselves in an attempt to appease God’s wrath.
However, fear of the plague also led to social tensions and the targeted persecution of minorities. Conspiracy theories about alleged well-poisoning made Jewish communities scapegoats, even though Jews died of the plague just as their Christian neighbours did. The first attacks began as early as 1348. On 14 February 1349, an estimated 2,000 Jews were murdered in Strasbourg – many of them burnt alive. In Worms, in March 1349, the Jewish community set fire to their own homes and chose to take their own lives to escape the threatened persecution; more than 580 deaths are recorded. Similar violence befell Jewish communities in Cologne, Basel, Erfurt and numerous other towns. Pope Clement VI expressly condemned the persecutions of 1348 in two papal bulls – yet his words fell on deaf ears. In many parts of Germany, Jewish communities barely existed for generations after 1353.
These acts of violence were often driven by economic motives: debts owed to Jewish creditors could thus ‘disappear’, and property was seized. These misinterpretations diverted resources towards persecution rather than effective measures to combat the plague – thereby accelerating its spread rather than containing it.
Medical knowledge, measures and quarantine in the Middle Ages
In the late Middle Ages, humoral pathology dominated medicine: the theory of the four humours, as expounded by Hippocrates and Galen, formed the basis of medical practice. No doctor of the time had even the faintest inkling of the plague bacterium. Instead, ‘bad air’ and unfavourable celestial alignments were regarded as the causes of disease. This limited medical knowledge led to largely ineffective measures.
The typical attempts at treatment reflect the state of knowledge at the time:
- Doctors would bleed patients to remove supposedly ‘corrupted’ blood.
- Emetics and enemas were frequently administered.
- Fragrances, incense and vinegar baths were intended to dispel the ‘bad air’.
- Pope Clement VI had aromatic substances burnt as a preventative measure and stood between two large fires.
An early prevention strategy was set out in the Paris Plague Treatise of 1348, drawn up by the Sorbonne’s Faculty of Medicine. It contained advice on keeping the air clean, avoiding crowds and fumigating houses. However, these recommendations reached only a small proportion of the population.
Early quarantine measures proved to be significantly more effective. In 1377, the city of Ragusa (now Dubrovnik) introduced a thirty-day waiting period for incoming ships and travellers from plague-stricken areas, known as the ‘trentino’. Venice later extended this period to forty days, known in Italian as ‘quarantena’ – from which the modern term ‘quarantine’ is derived. Plague houses and lazarettos were set up outside the city walls, the sick were isolated, and affected houses were marked.
These measures were partially effective, as they reduced interpersonal contact. However, without controlling the actual carriers – rats and fleas – they were unable to prevent major outbreaks. Systematic legal regulations for combating epidemics only emerged gradually over the following centuries.
Demographic, economic and political consequences of the spread of the plague
The Black Death led to a massive decline in Europe’s population. Entire villages were deserted, farms lay fallow, and the age and gender structure of entire regions shifted noticeably. In some cases, the death toll was so high that in certain areas there were not enough people left to bury the dead properly.
The economic repercussions were far-reaching:
| Area | Change |
|---|---|
| Labour force | Massive shortage due to the sharp decline in population |
| Wages | Significant rise in wages following the plague due to labour shortages |
| Agriculture | Shift from arable farming to livestock farming in parts of Europe |
| Innovation | Increased mechanisation, for example in ploughing and milling |
| Feudal system | The loosening of feudal ties and serfdom |
The labour shortage following the Black Death led to economic upheavals that shaped the entire late Middle Ages. Survivors were able to demand significantly higher wages, and opportunities for social mobility increased noticeably.
Politically, the Plague led to a considerable loss of authority for the Church – after all, prayers and processions had failed to halt the epidemic. Social tensions erupted in peasant uprisings, such as the French Jacquerie of 1358 and the English Peasants’ Revolt of 1381. This permanently shifted the balance of power between the nobility, the Church and the population.
Overall, the Plague acted as a turning point between the Middle Ages and the early modern period. Culturally, there was a deepening focus on death and transience: motifs of the Dance of Death and memento mori depictions characterised the art of the era. At the same time, the catastrophe provided indirect impetus for educational and reform movements that later culminated in the Renaissance and the Reformation. In the long term, the Plague thus also contributed to improvements in healthcare – a bitter but real step forward.

Recurring waves of the plague and the end of the great epidemics in Europe

The Black Death was not the end of the plague in Europe. The disease remained endemic for several centuries, and recurring plague epidemics characterised the late Middle Ages and the early modern period.
An overview of major outbreaks:
- 14th and 15th centuries: regular local epidemics at intervals of around ten to twenty years
- 1665/66: the Great Plague of London, which claimed tens of thousands of lives
- 1708–1714: severe waves of the plague in northern and eastern Europe, including Prussia, Poland and Russia
- 1720–1722: the last major Western European epidemic in Marseille and Provence
There are many reasons for the gradual disappearance of major plague epidemics in Europe. Improved urban hygiene and waste disposal made it harder for rats to breed. Architectural changes – sturdier houses, better storage facilities – reduced contact between humans and rodents. Institutionalised public health authorities and quarantine systems provided, for the first time, systematic solutions for disease control. Biological changes in rat populations and in the pathogen itself may also have played a role.
At the end of the 19th century, the third plague pandemic began in the Chinese province of Yunnan. It spread worldwide via port cities such as Hong Kong and hit India particularly hard. However, Europe was no longer affected to the same extent as it had been centuries earlier.
The plague today: prevalence, modern medicine and the significance of its history
The plague as a disease has not been eradicated. Even today, Yersinia pestis exists in natural reservoirs, particularly in rural regions of Africa, Asia and the Americas. The World Health Organisation (WHO) lists the Democratic Republic of the Congo, Madagascar and Peru as the countries with the highest number of reported cases. Isolated cases also occur in Mongolia and parts of the USA. Worldwide, the WHO estimates that there are between 1,000 and 3,000 reported cases per year.
Modern medicine now offers effective treatments:
- Diagnosis: Laboratory tests such as blood culture and PCR enable rapid identification of the pathogen.
- Treatment: Antibiotics such as streptomycin and doxycycline reduce the case-fatality rate for treated bubonic plague to around 10 to 15 per cent; without treatment, it is significantly higher.
- Prevention: Control of rodent and flea populations, public health education in endemic areas, and mandatory reporting of suspected cases.
An outbreak in Madagascar in 2017 highlights the continuing significance of this issue: according to official figures, by the end of the acute phase of the outbreak, around 2,400 confirmed, probable and suspected cases had been reported, with 209 deaths. A large proportion of these cases involved the particularly dangerous pneumonic plague. Early detection remains crucial – especially in the case of pneumonic plague, which is almost always fatal if left untreated.
The historical understanding of how the plague spread – the role of trade, mobility, ecology and social inequality – also provides important insights into how to deal with modern pandemics. The Covid-19 pandemic has shown that global interconnectedness can facilitate the spread of epidemics. However, modern science and healthcare systems now offer possibilities that did not exist in the Middle Ages. The history of the spread of the plague demonstrates how crucial transparent communication, functioning infrastructure and international cooperation are for containing epidemics and pandemics.
Conclusion: What the history of the spread of the plague teaches us
The history of the spread of the plague stretches from its origins in rodent reservoirs in Central Asia, through the devastating Black Death in Europe, to modern control measures involving antibiotics and public health interventions. What began as a local outbreak in the Tian Shan Mountains in Kyrgyzstan became the greatest catastrophe of the Middle Ages as a result of trade routes, wars and a lack of knowledge.
The key lessons from this history can be summarised briefly: scientific understanding of pathogens and transmission routes forms the basis of any effective disease control. Transparent communication must replace the search for scapegoats and persecution. And hygiene, infrastructure and social justice play a decisive role in determining the course of epidemics and pandemics.
The history of the plague vividly illustrates how closely the environment, trade, politics and medicine are intertwined. Historical experiences help us to better understand and manage future pandemics. From the medieval Black Death to today’s globalised world, the following holds true: those who know the past are better prepared for the future.
Frequently Asked Questions about the Spread of the Plague (FAQ)
Why were some regions of Europe less severely affected by the plague?
Differences in population density, less involvement in long-distance trade networks and, in some cases, quicker isolation measures helped to slow the spread locally. Sources report comparatively milder effects in parts of Poland, Bohemia and some rural regions. However, the historical record is patchy, and no area in Europe was completely spared. The scale and timing varied greatly from region to region – depending, in part, on the routes of trade.
Was it possible to be immune after surviving the plague?
Anyone who survived a plague infection could certainly develop a certain degree of immunity. Antibodies and cellular immune responses develop, but their strength depends on the form and severity of the infection. There was no absolute, lifelong immunity – re-infection remained possible. In the Middle Ages, these mechanisms were unknown and were reflected in the sources, at best, as vague observations: ‘Some people did not fall ill a second time.’ Systematic knowledge of the matter was completely lacking.
What role did diet and general health play in the spread of the disease?
Malnutrition and recurring famines – such as the Great Famine of 1315 to 1317 – increased the population’s susceptibility to infection. Weakened bodies were less able to fight off the pathogen. Although the more affluent classes were more likely to be able to flee to the countryside, they were by no means safe from infection. The combination of poverty, poor living conditions and high mortality runs as a consistent pattern throughout the entire history of the plague.
Are there still genetic traces of the plague in the European population today?
Recent studies suggest that the Black Death may have favoured certain genetic variants linked to immune responses. Epidemics can influence the genetic profile of a population in the long term – a process that researchers describe as natural selection under extreme pressure. However, research in this area is still ongoing, and not all connections are considered to have been conclusively established.
Could the Black Death return in a similar form?
Yersinia pestis continues to exist in natural reservoirs, and local outbreaks remain possible. However, a global catastrophe on the scale of the 14th century is highly unlikely due to modern medicine, existing reporting requirements and effective antibiotic treatments. International cooperation via the WHO and national health authorities can now effectively contain major outbreaks. At the same time, other emerging pathogens show that diseases capable of causing pandemics continue to pose a real threat. The lessons from the history of the plague therefore remain relevant to today’s health policy.


Letters from the trading house
New arrivals, market dates and offers, straight from Rinchnach. Unsubscribe any time with one click.
Subscribe to the newsletter